

Home › Knowledge Hub › Antimicrobial Stewardship › AMS Compliance Under the New Aged Care Quality Standards
Antimicrobial Stewardship
By Lyndon Forrest, Managing Director · Clinically reviewed by Bridgette Mackie & Dianne Newey, Clinical Directors · April 2026 · 15 min read
AMS Compliance Under the New Aged Care Quality Standards
TL;DR — – Quick Summary
From 1 November 2025, AMS compliance is a statutory condition of registration under the Aged Care Act 2024. All Category 5 (nursing/transition care) and Category 6 (residential care) providers must implement an AMS system under Action 5.2.1 of the Strengthened Aged Care Quality Standards.
Action 5.2.1 requires providers to implement ‘an antimicrobial stewardship system that complies with contemporary, evidence-based practice and is relevant to the service context.’ ACQSC audits use graded ratings – major non-conformance can result in registration conditions or revocation.
This article explains what Action 5.2.1 requires, how it maps to the AMS Clinical Care Standard’s 8 Quality Statements, how different provider categories are audited, and what evidence auditors will look for.
What Are the AMS Requirements Under the New Aged Care Quality Standards?
From 1 November 2025, all residential aged care providers are legally required to implement an antimicrobial stewardship (AMS) system under Action 5.2.1 of the Strengthened Aged Care Quality Standards, which form part of the Aged Care Act 2024.
| “The provider implements an antimicrobial stewardship system that complies with contemporary, evidence-based practice and is relevant to the service context.” – Action 5.2.1, Strengthened Aged Care Quality Standards (August 2025), effective 1 November 2025 |
|---|
This requirement applies to all providers registered in Categories 5 and 6 – nursing and transition care, and residential care. All existing residential aged care facilities (RACFs) in Australia were automatically deemed into Category 6 when the new Act commenced on 1 November 2025. Compliance with the Strengthened Standards is a condition of registration – not a best-practice aspiration.
Action 5.2.1 was introduced following Recommendations 18-21 of the Royal Commission into Aged Care Quality and Safety (2021), which identified clinical care – including AMS and IPC – as an area requiring specific, measurable standards. The previous Quality Standards contained no action specifically requiring AMS.
Source: Aged Care Quality and Safety Commission (2025); Department of Health and Aged Care (August 2025)
What Changed Under the Aged Care Act 2024? Before and After Comparison
The table below compares key changes relevant to AMS and IPC compliance between the previous Quality Standards (until 31 October 2025) and the Strengthened Standards (from 1 November 2025).
| Area | Previous Standards (pre-Nov 2025) | Strengthened Standards (from 1 Nov 2025) |
|---|---|---|
| AMS requirement | No specific AMS action; general clinical care expectation only | Explicit Action 5.2.1: implement an AMS system complying with contemporary evidence-based practice |
| IPC requirement | General expectation of safe environment; no dedicated IPC outcome | Outcome 4.2 (10 actions) for IPC in care environment + Outcome 5.2 for IPC in clinical care |
| IPC Lead role | Recommended in IPC guidelines but not referenced in the Standards | Action 5.2.2 references IPC Lead as part of documented IPC system roles and responsibilities |
| Audit type | Quality reviews every 3 years; compliant/non-compliant rating | Registration and renewal audits; graded ratings: conformance / minor / major non-conformance / exceeding |
| Enforcement powers | No power to revoke approval for non-compliance | ACQSC can impose registration conditions or revoke registration for non-conformance |
| Governing body accountability | Board oversight expected but not explicit in Standards | Standard 2 explicitly requires governing body to endorse and monitor clinical governance including AMS |
| Consumer rights | Charter of Aged Care Rights | New Statement of Rights – provider must show AMS decisions respect older person preferences |
Source: Strengthened Aged Care Quality Standards (DoH, August 2025); ACQSC Strengthened Quality Standards webpage; New Regulatory Model Guidance (DoH, December 2025)
The most significant changes for AMS compliance are: (1) the introduction of an explicit AMS action (5.2.1) for the first time; (2) graded audit ratings that make non-conformance visible; and (3) expanded ACQSC enforcement powers – including registration revocation – not available under the previous model.
Where Does AMS Sit Within the Seven Strengthened Standards?
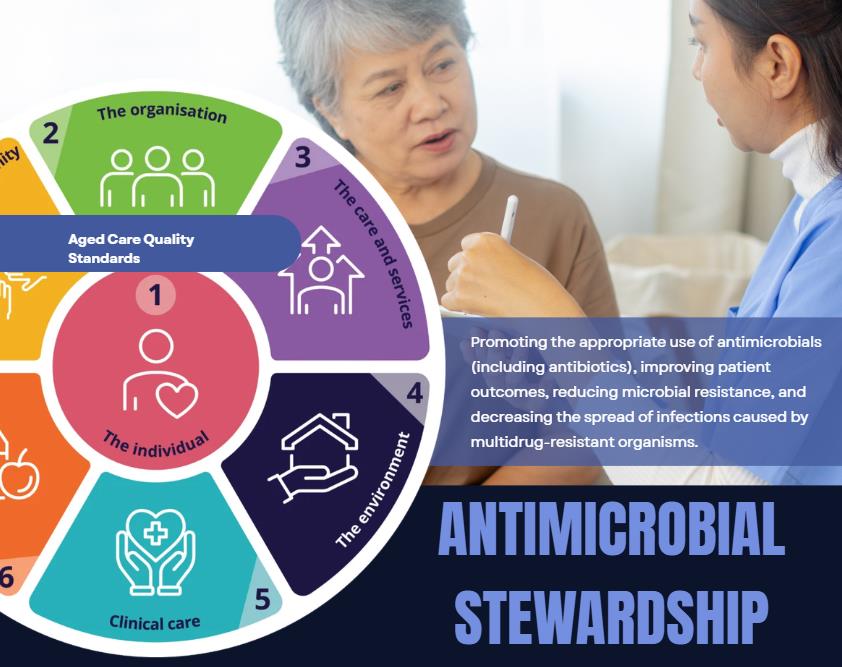
AMS compliance is primarily located in Standard 5: Clinical Care, Outcomes 5.2 and 5.3. However, AMS connects to obligations across multiple standards – from governing body accountability (Standard 2) to consumer rights (Standard 1).
| Std | Title | AMS/IPC Relevance |
|---|---|---|
| 1 | The Individual | Informed consent for antimicrobials; consumer communication about AMS |
| 2 | The Organisation | Governing body must endorse AMS policy and monitor performance |
| 3 | Care and Services | Clinical care planning integrates infection risks; Actions 3.1.6, 3.2.1 |
| 4 | The Environment | Outcome 4.2: IPC system for care environment – 10 Actions including IPC Lead |
| 5 | Clinical Care (PRIMARY) | Outcome 5.2: AMS (Action 5.2.1) and IPC in clinical care (Action 5.2.2). Outcome 5.3: Safe and quality use of medicines |
| 6 | Food and Nutrition | Indirect – nutrition supports immune function and recovery from infection |
| 7 | The Residential Community | Outbreak communication; resident and family involvement in AMS decisions |
Source: Strengthened Aged Care Quality Standards (DoH, August 2025); Guidance for Standard 5 (ACQSC, 2025)
Need help implementing this in your facility? The IPS Hub gives your IPC Lead instant access to ready-made policies, procedures, and audit tools — updated monthly.
What Is the Difference Between Outcome 4.2 (IPC) and Outcome 5.2 (AMS/Clinical IPC)?
Many providers are confused about the relationship between Outcome 4.2 and Outcome 5.2. They are related but distinct obligations. Outcome 4.2 covers general IPC in the care environment. Outcome 5.2 specifically covers IPC in clinical care services – and introduces the AMS requirement through Action 5.2.1.
| Outcome 4.2 – IPC in Care Environment | Outcome 5.2 – IPC/AMS in Clinical Care | |
|---|---|---|
| Standard | Standard 4: The Environment | Standard 5: Clinical Care |
| Core focus | Environmental and general infection control in all service settings | Clinical procedure-specific IPC + AMS; where clinical care is provided |
| Number of Actions | 10 Actions (4.2.1 to 4.2.10) | 2 Actions: 5.2.1 (AMS) + 5.2.2 (IPC in clinical care) |
| AMS requirement? | No – Outcome 4.2 does not include AMS | Yes – Action 5.2.1 is the AMS compliance obligation |
| Key tool | Aged Care IPC Guide (ACSQHC/ACQSC, Version 1.1, January 2025) | AMS SAT (ACQSC); AMS CCS Guidance (ACSQHC, November 2024); AC-NAPS |
Source: Guidance for Standard 5 (ACQSC, 2025); Aged Care IPC Guide Version 1.1 (ACSQHC/ACQSC, January 2025)
The practical implication: residential care providers need to satisfy both Outcome 4.2 and Outcome 5.2. The AMS SAT maps primarily to Outcome 5.2 Action 5.2.1. The Aged Care IPC Guide maps to Outcome 4.2. Both are assessed in a Category 6 audit.
What Does Action 5.2.1 Require Providers to Have in Place?
The guidance for Action 5.2.1 (ACQSC, 2025) identifies seven components that constitute a documented AMS system. These are the associated activities against which an auditor assesses conformance.
| Required Component | What This Means in Practice | Evidence Auditors Will Look For |
|---|---|---|
| Policies and procedures for appropriate antimicrobial use | Facility-specific AMS policy – not just a reference to TG Antibiotic. Must address indication, duration, stop date, review | AMS policy document; dated and signed; reviewed <=12 months ago |
| Roles and responsibilities for AMS | Named AMS lead (IPC Lead or DOC); GP/NP prescribing responsibilities; pharmacist role; nursing roles documented | Organisational chart or policy; role descriptions; staff aware of their role |
| Clinical review and specialist referral processes | Protocol for when to escalate to GP/NP; process for microbiology result review; telehealth pathway for specialist input | Clinical escalation flowchart; GP communication template; microbiology review log |
| Access to external AMS expertise | Arrangements for consulting infectious disease physician, microbiologist, or clinical pharmacist for complex cases | Contract or service agreement; documented cases of external referral; pharmacist RMMR/QUM |
| AMS education and training system | Annual AMS training for all clinical staff; GP education on local prescribing patterns | Training register; competency records; evidence GPs received facility AMS data |
| Monitoring and reporting processes | Regular audit of antimicrobial prescribing (AC-NAPS or local audit); reporting to governing body at least quarterly | AC-NAPS certificate or local audit records; quarterly board/clinical governance reports |
| Quality improvement processes | Identified AMS issues translated into documented QI actions with review dates | QI register or AMS SAT action plan; evidence of completed improvement cycles |
Source: Guidance for Standard 5, Outcome 5.2, Action 5.2.1 Associated Activities (ACQSC, 2025); AMS SAT User Guide v3 (ACQSC)
| What ‘Relevant to the Service Context’ Means For all residential care providers (Category 6): implement the full AMS system across all seven components. For home care providers with clinical antimicrobial involvement (Category 5): implement a full AMS system. Focus on antimicrobial ordering, prescriber engagement, and monitoring. For home care providers without prescribing/supply/administration: focus on staff education about appropriate antimicrobial use and consumer information to support informed decisions with prescribers. |
|---|
How Does the AMS Clinical Care Standard Relate to Action 5.2.1?
The Antimicrobial Stewardship Clinical Care Standard (AMS CCS), published by ACSQHC, directly supports Action 5.2.1. The ACSQHC Guidance for Implementation of the AMS Clinical Care Standard in Aged Care (November 2024) states: ‘This guidance also supports implementation of the strengthened Aged Care Quality Standards, which include an action on AMS.’ Demonstrating alignment with all 8 Quality Statements is strong evidence for Action 5.2.1 conformance.
| Quality Statement | Core Requirement | Key Aged Care Application |
|---|---|---|
| QS 1 – Life-threatening infection | Appropriate antimicrobial given immediately without waiting for test results | Nurses trained in sepsis recognition; clinical escalation protocol with GP/NP contact pathway |
| QS 2 – Guideline-concordant prescribing | Antimicrobials prescribed per Therapeutic Guidelines or locally endorsed guidelines | Access to current TG Antibiotic (electronic); no broad-spectrum without ID input |
| QS 3 – Allergy/adverse reaction documentation | Allergy assessed and documented; enables safest antimicrobial choice | Check healthcare records before prescribing; unknown allergies explicitly documented |
| QS 4 – Microbiology sampling | Appropriate samples taken before starting antimicrobials; avoid low-value testing | No urine dipstick without clinical UTI signs; UTI clinical pathway in place |
| QS 5 – Consumer information | Patient informed about condition, treatment options, risks, how to use antimicrobials | ‘Do you need antibiotics?’ fact sheet; discuss C. difficile risk; shared decision-making |
| QS 6 – Documentation | Indication, active ingredient, dose, frequency, route, intended duration documented | Antimicrobial ordering form; stop/review date required on every prescription |
| QS 7 – Regular clinical review | Therapy reviewed regularly; microbiology results reviewed promptly; therapy adjusted | GP/NP review microbiology within 24h; RMMR/QUM pharmacist involvement |
| QS 8 – Antimicrobial prophylaxis | Surgical/procedural prophylaxis per current guidelines | No antibiotics for routine catheter care; dental procedures follow TG guidance |
Source: Guidance for Implementation of the AMS Clinical Care Standard in Aged Care (ACSQHC, November 2024); Therapeutic Guidelines: Antibiotic (eTG)
| Quality Statement 4 – Highest Priority Action Avoiding urine dipstick testing without clinical signs of UTI is the single highest-priority AMS action for most RACFs. Up to 60% of antimicrobial prescribing in RACFs relates to suspected UTIs (ACSQHC, 2023), and approximately half is for asymptomatic bacteriuria (ASB) – which does not require treatment. A UTI clinical pathway aligned with QS 4 is both an AMS compliance action and the highest-impact intervention available to most facilities. |
|---|
Which Australian Providers Must Comply, and How Are They Audited?
The Aged Care Act 2024 introduced six registration categories. The Strengthened Aged Care Quality Standards apply as a condition of registration for providers in Categories 4, 5, and 6 only. All existing residential aged care providers were automatically deemed into Category 6 on 1 November 2025.
| Category | Services Covered | AMS Obligation (Action 5.2.1) |
|---|---|---|
| 1 – Home & community | CHSP domestic assistance, social support, transport | Not applicable – Standards do not apply |
| 2 – Assistive technology | Equipment, home modifications | Not applicable – Standards do not apply |
| 3 – Advisory & support | Information and advisory services | Not applicable – Standards do not apply |
| 4 – Personal & care support | Personal care, community care packages with clinical components | AMS education and consumer information focus |
| 5 – Nursing & transition care | Nursing care, transition care programs, clinical services in community | Full Action 5.2.1 applies; AMS policy, education, monitoring required |
| 6 – Residential care (PRIMARY) | All RACFs; all existing RACF providers deemed to Category 6 on 1 Nov 2025 | Full Action 5.2.1 applies; AC-NAPS strongly indicated; AMS SAT the primary compliance tool |
Source: How the Aged Care Regulatory Model Works (DoH, February 2026); Registration Model (ACQSC, 2025); New Regulatory Model Guidance for Residential Providers (DoH, December 2025)
What Are the Audit Ratings and What Do They Mean for AMS?
ACQSC audits are forward-looking – they assess whether systems and processes demonstrate that conformance is achievable and sustainable, not just whether a policy exists today. The rating for Outcome 5.2 is the key AMS compliance measure.
| Rating | What It Means | Typical AMS Evidence |
|---|---|---|
| Exceeding (Cat. 6 renewal only) | Provider conforms with all Standards and demonstrates excellence | Full AMS system; AC-NAPS participation with trend analysis; completed QI cycles; board AMS reports; consumer education active |
| Conformance | Provider demonstrates it can meet the Standards | AMS SAT completed with action plan; AMS policy in place; staff training records; monitoring process established |
| Minor non-conformance | Provider mostly meets the Standards but has gaps | AMS policy exists but not facility-specific; monitoring not yet implemented; AC-NAPS not yet completed |
| Major non-conformance | Provider does not demonstrate it can meet the Standards | No AMS policy; no documented roles; no monitoring; no staff AMS training; urine dipstick routinely used without clinical criteria |
Source: Strengthened Quality Standards – Assessing Performance and Managing Non-Conformance (ACQSC, 2025); Audit Overview (ACQSC, 2025)
What Does an ACQSC Audit Actually Involve?
Stage 1 – Pre-audit: Provider submits documentary evidence of systems and processes. For AMS: the AMS policy, AMS SAT results and action plan, training records, and monitoring reports.
Stage 2 – Audit delivery: ACQSC visits each site for Category 6 providers. Auditors meet governing body and senior management, test whether systems are embedded in practice – reviewing resident medication records, interviewing clinical staff, and reviewing board reports.
Stage 3 – Audit report: Preliminary report with performance ratings for each outcome. Providers can respond before the final report is issued, which informs the registration decision.
| Minor Non-Conformance Is Not a Failure – But It Does Require Action ACQSC guidance notes that minor non-conformances are expected to be common during the transition period. For AMS-related minor non-conformances, a provider will typically need a credible action plan with timelines – e.g., ‘AMS SAT to be completed by [date]; AC-NAPS participation registered by [date].’ Major non-conformance on Outcome 5.2 – indicating no effective AMS system – represents a significant clinical risk finding and makes regulatory action more likely. |
|---|
Explore Related IPS Resources
This article is part of the IPS Knowledge Hub Antimicrobial Stewardship in Aged Care topic cluster.
- Pillar: Antimicrobial Stewardship in Aged Care
- Cluster 1.1: AMS Programme Setup Guide for RACFs
- Cluster 1.2: AMS Compliance Under the New Aged Care Quality Standards
- Cluster 1.3: The UTI Clinical Pathway for RACFs
- Cluster 1.4: AMS Monitoring and Reporting in Aged Care (coming soon)
AMS & IPC Training: Stop the Spread — join our expert-led workshop combining Antimicrobial Stewardship and IPC strategies designed specifically for aged care facilities.
Frequently Asked Questions
What are the new aged care quality standards 2025?
The Strengthened Aged Care Quality Standards took effect on 1 November 2025 under the Aged Care Act 2024. They replace the previous 2019 Standards and introduce seven standards with graded audit ratings, explicit AMS and IPC actions, expanded governing body accountability, and strengthened ACQSC enforcement powers.
Is AMS compliance mandatory under the new aged care standards?
Yes. Action 5.2.1 requires all Category 5 and 6 registered providers to implement an AMS system as a statutory condition of registration. Non-compliance can result in registration conditions or revocation by the ACQSC.
What AMS tool should we use to demonstrate compliance?
The AMS Self-Assessment Tool (AMS SAT), published by the ACQSC, is the primary compliance tool for residential aged care providers. Use it alongside the ACSQHC Guidance for Implementation of the AMS Clinical Care Standard in Aged Care (November 2024), which maps the 8 Quality Statements to practical aged care actions.
What is the difference between the AMS SAT and AC-NAPS?
The AMS SAT is a self-assessment tool that maps your facility’s systems against the 7 components of Action 5.2.1. AC-NAPS is a national prescribing surveillance program – it generates prescribing data to support monitoring and reporting, which is one of the 7 AMS SAT components. Both are important; AC-NAPS participation is strongly indicated for Category 6 providers.
What happens if an aged care provider fails the AMS audit?
Under the Aged Care Act 2024, the ACQSC has expanded enforcement powers. Minor non-conformance typically results in registration conditions with a requirement to demonstrate improvement. Major non-conformance – no effective AMS system – can result in registration conditions, mandatory external management, or revocation of registration.
Does Action 5.2.1 apply to home care providers?
Yes, but with scaled expectations. The guidance distinguishes between home care providers with clinical antimicrobial involvement (full AMS system required) and those who do not prescribe, supply, or administer antimicrobials (focus on staff education and consumer information). All residential care providers (Category 6) must implement the full AMS system across all 7 components of the AMS SAT.
References and Further Reading
- Australian Commission on Safety and Quality in Health Care (ACSQHC). Guidance for Implementation of the AMS Clinical Care Standard in Aged Care. November 2024. safetyandquality.gov.au
- Aged Care Quality and Safety Commission (ACQSC). Strengthened Aged Care Quality Standards. agedcarequality.gov.au
- Aged Care Quality and Safety Commission (ACQSC). Guidance for Standard 5: Clinical Care. 2025.
- Aged Care Quality and Safety Commission (ACQSC). Audit Overview – Strengthened Quality Standards.
- Australian Government Department of Health and Aged Care. Strengthened Aged Care Quality Standards – August 2025. health.gov.au
- Australian Government Department of Health and Aged Care. New Regulatory Model – Guidance for Residential Aged Care Providers. December 2025.
- Aged Care Quality and Safety Commission / ACSQHC. Aged Care IPC Guide Version 1.1. January 2025.
In This Article
- What Are the AMS Requirements Under the New Aged Care Quality Standards?
- What Changed Under the Aged Care Act 2024? Before and After Comparison
- Where Does AMS Sit Within the Seven Strengthened Standards?
- What Is the Difference Between Outcome 4.2 (IPC) and Outcome 5.2 (AMS/Clinical IPC)?
- What Does Action 5.2.1 Require Providers to Have in Place?
- How Does the AMS Clinical Care Standard Relate to Action 5.2.1?
- Which Australian Providers Must Comply, and How Are They Audited?
- What Are the Audit Ratings and What Do They Mean for AMS?
- What Does an ACQSC Audit Actually Involve?
- What are the new aged care quality standards 2025?
- Is AMS compliance mandatory under the new aged care standards?
- What AMS tool should we use to demonstrate compliance?
- What is the difference between the AMS SAT and AC-NAPS?
- What happens if an aged care provider fails the AMS audit?
- Does Action 5.2.1 apply to home care providers?
About the Author
Lyndon Forrest is the Managing Director of Bug Control — Infection Prevention Services, with over 30 years’ experience supporting aged care facilities across Australia and New Zealand with infection prevention, antimicrobial stewardship, and accreditation readiness.
Clinically reviewed by Bridgette Mackie & Dianne Newey, Clinical Directors
AMS & IPC Training
Stop the Spread — join our expert-led workshop combining Antimicrobial Stewardship and IPC strategies designed specifically for aged care facilities.
Ready to Strengthen Your Facility’s Infection Prevention?
The IPS Hub provides aged care facilities across Australia and New Zealand with continuously updated IPC policies, AMS tools, outbreak management resources, and direct support from experienced IPC professionals.

